Sometimes the most interesting question begins with two stories that don’t seem to belong together. I was present when Herb Roi Richards spoke with an individual who said he had “cured himself” of hepatitis B using chlorine dioxide. Those were his words, and they represent his personal account, not a conclusion established by clinical research.
More recently, I heard another person describe something quite different. He said that after using chlorine dioxide orally, his previously diagnosed fatty liver had returned to normal.
Then I went back to Herb’s work. Herb also discusses chlorine dioxide in connection with liver cancer. Cirrhosis doesn’t appear to receive the same attention.
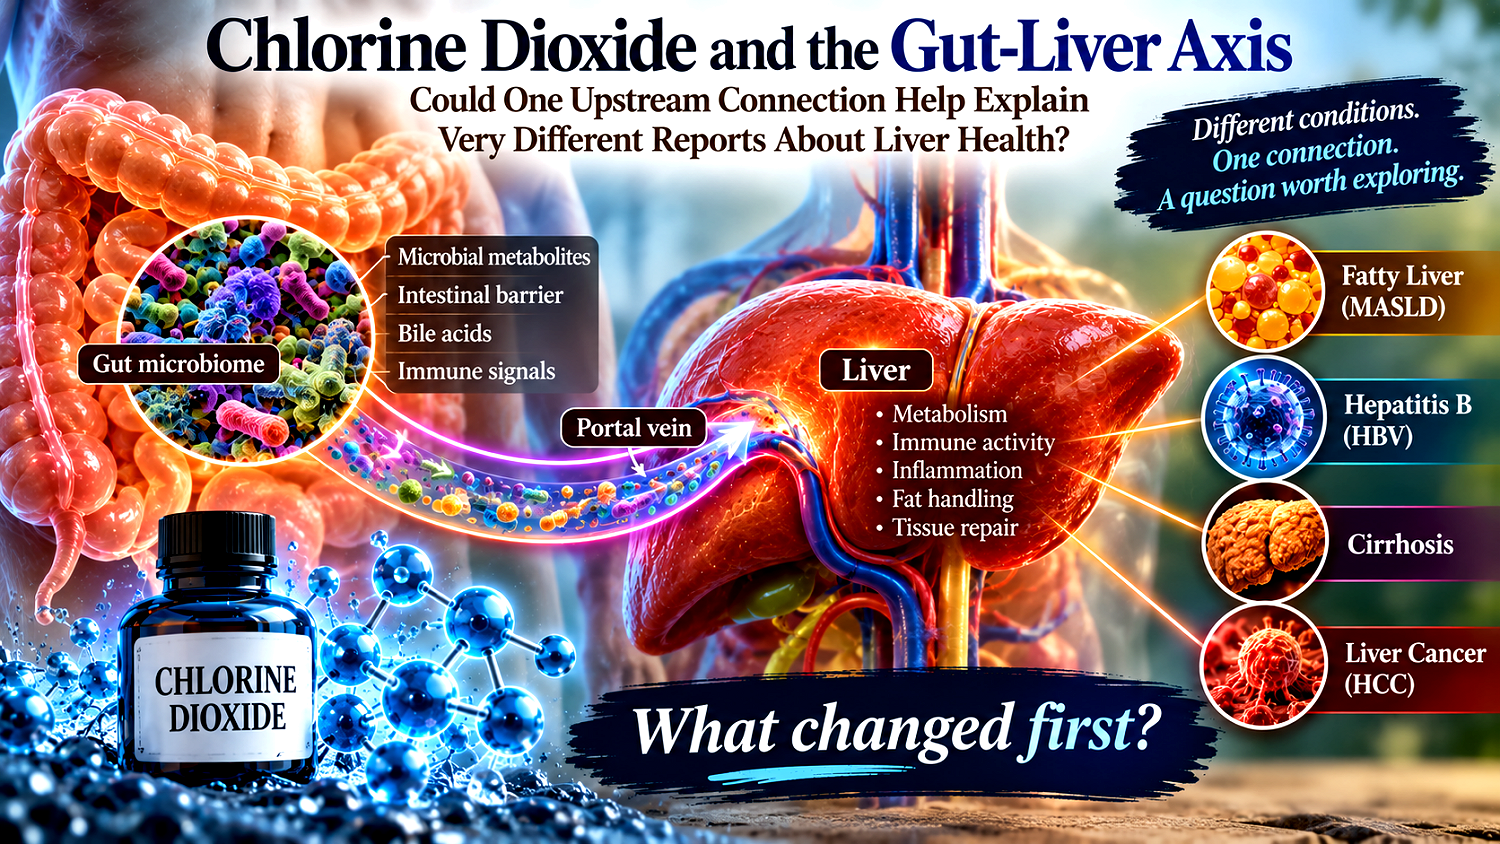
At first glance, hepatitis B, fatty liver, cirrhosis, and liver cancer look like four very different subjects. They are. But they also share something fascinating.
The liver is directly downstream from the gut. And that connection, known as the gut-liver axis, has become an important area of modern medical research.
Could it provide a clue for understanding some of these otherwise puzzling chlorine-dioxide reports? We don’t know. But there is enough happening in contemporary liver research to make the question worth exploring.
Your Liver Is Listening to Your Gut All Day Long
The gut-liver connection isn’t merely a clever metaphor. It’s plumbing. Blood leaving much of the gastrointestinal tract flows through the portal vein directly to the liver. Approximately 75% of the liver’s blood supply comes through this route.
That makes the liver one of the first major organs exposed to nutrients and microbial metabolites absorbed from the intestine. Communication also runs in the opposite direction: the liver sends bile acids and other substances back into the intestine, where they interact with intestinal microbes. PubMed Central (PMC)
That’s the gut-liver axis.
At its simplest:
GUT
↓
microbiome
↓
intestinal barrier
↓
microbial products and metabolites
↓
PORTAL VEIN
↓
LIVER
And the liver communicates back through bile acids, immune factors, and other signals. It’s a conversation taking place continuously.
The Gut Isn’t Sending Only Bacteria
This is where the subject gets considerably more sophisticated. When researchers talk about the microbiome affecting the liver, they aren’t necessarily saying bacteria themselves migrate from the intestine and attack the liver.
The intestinal ecosystem produces an enormous collection of biologically active substances. These include short-chain fatty acids, bile-acid derivatives, and other metabolites. Under unhealthy circumstances, increased intestinal permeability may also increase hepatic exposure to microbial components such as lipopolysaccharide.
Those signals can influence: inflammation, immune activity, insulin sensitivity, fat metabolism, bile-acid metabolism, and potentially fibrosis.
Recent MASLD research specifically identifies intestinal-barrier integrity, microbial metabolites, and gut-derived products as important components of the gut-liver relationship. PubMed
So, when something changes substantially in the intestinal environment, it isn’t unreasonable to ask whether the liver notices. It almost certainly does. The harder question is what changed and whether the change helped or hurt.

Fatty Liver: Probably Our Easiest Place to See the Connection
Fatty liver disease is now commonly described using the term metabolic dysfunction-associated steatotic liver disease, or MASLD. It isn’t simply caused by the microbiome.
Body weight, insulin resistance, diet, genetics, physical activity, diabetes, and other metabolic factors can all play important roles. But gut-liver research has added another dimension.
Recent reviews describe the gut microbiome as an important disease modifier in MASLD, with microbial metabolites, intestinal-barrier dysfunction, immune activation, and hepatic metabolism all interacting. PubMed
That makes the report I recently heard interesting.
Someone says: “I had fatty liver. I used chlorine dioxide. Later my liver was normal.” That doesn’t establish that chlorine dioxide reversed the fatty liver.
A person could simultaneously lose weight, improve insulin sensitivity, change diet, exercise more, reduce alcohol consumption, or experience any number of other changes. But unlike some subjective health reports, fatty liver gives researchers plenty to measure.
We can look at:
- Liver imaging.
- Liver fat.
- ALT and AST.
- Fibrosis measurements.
- Blood glucose
- HbA1c
- Triglycerides
- .Weight
- Waist circumference.
- And increasingly, we can simultaneously examine the person’s intestinal microbiome and microbial metabolites.
That presents an intriguing possibility.
What if we stopped asking only whether the liver improved and started asking what changed before it improved?
That’s a much better experiment.
Hepatitis B: A Very Different Liver Problem
Hepatitis B requires a different discussion. HBV is a virus that infects liver cells. It would therefore be inappropriate to take an anecdote about someone using chlorine dioxide and conclude: chlorine dioxide fixed his gut, therefore his hepatitis B disappeared.
First, we’d need to establish what “cured” actually meant.
- Did his ALT normalize?
- Did HBV DNA become undetectable?
- Did hepatitis B surface antigen – HbsAg – disappear?
- Did he achieve what’s called a functional cure?
Those aren’t interchangeable outcomes.
But here’s where our investigation took an unexpected turn.
Researchers Are Already Studying the Gut in Hepatitis B
A 2025 human study examined the intestinal microbiomes of people with chronic hepatitis B, including patients who achieved functional cure.
Researchers found microbial differences associated with functional cure and went further, examining short-chain fatty acids produced by identified bacteria in an HBV laboratory model. PubMed
That doesn’t mean gut bacteria cure hepatitis B. But it tells us researchers are seriously investigating whether intestinal microbial ecology influences the host-virus relationship.
Then things become even more interesting.
Someone Already Tried Changing the Microbiome
A small pilot study investigated fecal microbiota transplantation – FMT – in people with chronic hepatitis B who remained HBeAg-positive despite more than a year of antiviral treatment.
Twelve participants completed six FMT cycles while continuing antiviral therapy; another 15 patients continued antiviral therapy as controls.
The investigators reported changes including HBeAg loss in some FMT recipients, while emphasizing the preliminary nature of the work. PubMed
That’s a tiny exploratory study. It certainly doesn’t establish FMT as a hepatitis-B cure, and a 2026 review describes FMT in chronic HBV as exploratory and, if useful, potentially adjunctive to antiviral therapy. PubMed
But for our investigation it establishes an important principle: Researchers have deliberately manipulated the intestinal microbiome to see whether something changes in a viral disease of the liver.
That’s quite a long way from saying the gut has nothing to do with hepatitis B.
Cirrhosis May Be Even More Interesting
Cirrhosis is another completely different situation. Cirrhosis involves significant structural scarring of the liver after prolonged injury. Changing intestinal bacteria doesn’t magically erase scar tissue. But cirrhosis and the intestinal ecosystem can become caught in an unfortunate feedback loop.
Liver disease can alter bile acids, immunity and intestinal conditions. The intestinal barrier can deteriorate. Microbial products can reach portal circulation more readily. Inflammation increases. Liver function deteriorates further. And the cycle continues.
Modern reviews now describe dysbiosis, abnormal immune regulation, metabolic changes, and gut-barrier dysfunction as important features across chronic liver diseases, including cirrhosis. PubMed
Here we can go beyond association.
Scientists Have Actually Manipulated the Gut in People With Cirrhosis
A systematic review and meta-analysis examined 21 randomized studies involving 1,699 people with cirrhosis receiving microbiome-targeted therapies.
Across the studies, these interventions were associated with reductions in hepatic encephalopathy risk, ammonia, endotoxin, and AST, along with a modest improvement in MELD scores. Not every measure of liver function improved. PubMed
That’s important. Changing the intestinal environment can produce measurable downstream changes in people with serious liver disease.
FMT has also been tested experimentally in cirrhosis.
An early randomized clinical trial involving people with cirrhosis and recurrent hepatic encephalopathy found fewer serious adverse events and further encephalopathy episodes in the FMT group, along with improved cognition and measurable microbiome changes. It was a small study and doesn’t establish FMT as routine cirrhosis treatment. PubMed
Subsequent trials have continued investigating the approach. PubMed
Once again: Change something upstream in the gut. Something downstream changes.
That doesn’t tell us anything yet about chlorine dioxide. But it tells us something extremely important about the highway we’re investigating.
Then We Arrive at Liver Cancer
Herb Roi Richards includes liver cancer among conditions for which he discusses chlorine dioxide. That is Herb’s position and belongs in the historical and practitioner record surrounding his work.
It is not established clinical evidence that chlorine dioxide treats liver cancer. Nevertheless, our gut-liver investigation doesn’t disappear when cancer enters the picture. Quite the opposite.
Hepatocellular carcinoma, or HCC, is the most common form of primary liver cancer, and the gut-liver axis is now an active area of HCC research.
Researchers are investigating how dysbiosis, microbial translocation, bile acids, bacterial metabolites, chronic inflammation, and immune signaling may influence the environment in which liver cancer develops and progresses. PubMed
A very recent 2026 review describes the progression from MASLD through inflammation, fibrosis, and cirrhosis to MASLD-associated HCC while examining how microbiome-related metabolic and immune pathways may participate along the way. PubMed
That’s fascinating. But there’s a distinction we should not lose.
Helping create an environment in which cancer is more or less likely to develop is not the same as eliminating an established tumor.
Similarly, changing the tumor’s immune or metabolic environment isn’t synonymous with curing cancer.
So Herb’s liver-cancer reports should remain exactly what they are: observations and claims worthy of investigation, not proof of treatment efficacy.
Four Diseases That Suddenly Don’t Look Quite So Unrelated
Now stand back and look at what we’ve assembled.
Fatty liver. Hepatitis B. Cirrhosis. Liver cancer.
Different diseases. Different causes. Different treatments. Different outcomes. But each intersects with the same biological highway.
GUT
↓
microbial ecosystem
↓
intestinal barrier
↓
microbial metabolites • bile acids • immune signals
↓
PORTAL CIRCULATION
↓
LIVER
↓
metabolism • immunity • inflammation • tissue environment
From there, completely different downstream problems can emerge depending upon the person.
That’s considerably more interesting than trying to prove four unrelated chlorine-dioxide claims.

Where Does Chlorine Dioxide Fit?
Here’s where we have to leave some question marks on the page. Chlorine dioxide is a reactive oxidant with established antimicrobial chemistry.
That makes this hypothetical pathway tempting:
ORAL CHLORINE DIOXIDE
↓
changes microorganisms in the gut
↓
improves microbiome
↓
improves gut-liver signaling
↓
liver improves
It’s wonderfully tidy. Unfortunately, we don’t presently have evidence establishing that sequence.
In particular: Antimicrobial does not automatically mean microbiome-improving.
The intestinal microbiome isn’t simply a collection of bad organisms waiting to be disinfected. It is an ecosystem.
Removing or suppressing organisms can produce beneficial effects, harmful effects, or effects we don’t yet understand. And chlorine dioxide is reactive enough that assuming exactly what happens after oral exposure would get ahead of the evidence.
So, the scientifically useful version needs a very large question mark:
chlorine dioxide exposure
↓
?
↓
change in intestinal microbial or chemical environment?
↓
change in barrier function, metabolites, bile acids or immune signaling?
↓
portal circulation
↓
change in hepatic environment?
↓
measurable clinical outcome?
Now we have a hypothesis.
Maybe We Shouldn’t Assume the Microbiome Is the Only Domino
There’s another trap worth avoiding. Suppose future research really did find measurable liver changes following chlorine dioxide exposure. That still wouldn’t automatically prove: “It was the microbiome.”
Something else might have changed first.
- Microbial metabolism.
- Particular metabolites.
- Gut-barrier permeability.
- Bile-acid signaling.
- Immune signaling.
- Oxidation-reduction chemistry.
- Dietary behavior occurring simultaneously.
- Or something we haven’t considered.
That’s why our question needs to remain broader than: “Which bacteria did chlorine dioxide kill?”
The better question is: What Changed First?
And fortunately, modern science has tools Wayne Rowland, Herb and other early experimenters simply didn’t have readily available.
We can measure microbial populations. Metagenomics. Metabolomics. Short-chain fatty acids. Bile acids. Inflammatory markers. Intestinal-barrier markers. Liver enzymes. Fibrosis. Liver fat. Viral load. Viral antigens. Tumor characteristics.
We don’t have to guess nearly as much anymore.
The Study
Suppose a group of researchers recruited people already intending to use chlorine dioxide and documented them prospectively rather than reconstructing stories afterward.
Before exposure, researchers could establish: stool microbiome + microbial metabolites + bile-acid profile + intestinal-barrier markers + inflammatory markers alongside disease-specific measurements.
For fatty liver: MRI-PDFF or other validated imaging + liver enzymes + fibrosis measurements + metabolic markers
For hepatitis B: HBV DNA + HBsAg + HBeAg/anti-HBe where applicable + ALT and other appropriate clinical markers
For cirrhosis: MELD-related measurements + ammonia + clinical events + fibrosis/liver-function assessments
Cancer would require an entirely different and much more carefully controlled oncological study.
Then repeat the measurements over time. Now suppose liver markers improve.
Interesting. But suppose something even more intriguing happens: a reproducible intestinal or metabolic change consistently occurs first.
Now we’ve discovered something considerably more useful than another testimonial. We’ve discovered a domino. And if nothing meaningful changes upstream despite changes in liver measurements? Then the gut-liver hypothesis becomes weaker, and we go looking elsewhere.
That’s how an observation becomes a testable idea.
FMT Gives Us an Important Clue
There’s another reason I’m increasingly fascinated by this approach. We’ve encountered fecal microbiota transplantation repeatedly while investigating apparently unrelated conditions. Not because FMT proves anything about chlorine dioxide. It doesn’t.
FMT is useful to our thinking because it provides an independent experiment: What happens when researchers deliberately change the intestinal ecosystem?
In chronic hepatitis B, researchers have tried it experimentally. PubMed
In cirrhosis with recurrent hepatic encephalopathy, randomized human studies have found measurable clinical effects. PubMed
In MASLD, microbiome-targeted interventions remain an active area of investigation, although results are heterogeneous and a 2026 review notes that FMT has not reliably improved liver fat or insulin resistance in unselected populations. PubMed
That’s actually useful precisely because it isn’t universally successful. The lesson isn’t: Fix microbiome → cure liver disease.
The lesson is: The gut can influence the liver enough that deliberately changing the intestinal ecosystem can produce measurable downstream effects.
That makes our question biologically plausible without pretending we’ve answered it.
Maybe Chlorine Dioxide Has Been Getting Too Much Credit
There’s another possibility consistent with our earlier investigations. Suppose someone takes chlorine dioxide. Something upstream changes. Then the liver does what the liver is designed to do.
Metabolism changes. Immune signaling changes. Inflammation changes. Cells respond. Repair processes operate.
The person sees the outcome and naturally concludes: “Chlorine dioxide healed my liver.”
Maybe. But another interpretation could eventually prove more accurate: Chlorine dioxide altered one condition that had been interfering with the body’s ability to regulate or repair itself.
That’s a much more complicated story. It also gives the human body considerably more credit. And at present, it remains a hypothesis, not an established explanation for the anecdotes that prompted this investigation.
Don’t Chase the Liver Disease. Follow the Dominoes
This may be the larger lesson. If somebody reports that chlorine dioxide changed fatty liver, hepatitis B, cirrhosis, or even cancer, our first question probably shouldn’t be: “How could chlorine dioxide possibly treat all those different diseases?” Maybe that’s the wrong question.
Perhaps we should ask: “Do any of these conditions share an upstream pathway that could have changed first?”
In this case, remarkably, they do.
- The gut and liver are anatomically connected.
- The microbiome communicates with the liver.
- The intestinal barrier matters.
- Microbial metabolites matter.
- Bile-acid signaling matters.
- Immune signaling matters.
Researchers are actively manipulating the intestinal ecosystem to investigate liver disease.
None of that proves that chlorine dioxide beneficially affects this pathway. But it gives us somewhere sensible to look.
From Stories to Studies
The gentleman I heard describe himself as having “cured” his hepatitis B has a story. The person reporting reversal of fatty liver has a story. Herb accumulated stories and observations of his own.
Those stories shouldn’t be transformed into scientific conclusions they cannot support. But neither must their only possible destination be the wastebasket.
- Repeated observations can become questions.
- Questions become hypotheses.
- Hypotheses become measurements.
- Measurements become evidence.
- And evidence eventually tells us which ideas survive.
- Maybe chlorine dioxide will turn out to have an interesting influence on the gut-liver axis.
- Maybe its reported liver effects will ultimately have an entirely different explanation.
- Maybe carefully controlled research won’t reproduce the reports at all.
All three possibilities are worth knowing.
But now, at least, we have a considerably better question than: “Does chlorine dioxide cure liver disease?”
We can ask: What changed first?
If something happening in the gut consistently precedes something changing in the liver, that’s a trail worth following. And for once, the trail doesn’t have very far to travel.
It goes almost directly from the intestine, through the portal vein – straight to the liver.
Informational notice: This article explores hypotheses and emerging gut-liver research. It does not establish chlorine dioxide as a treatment for hepatitis B, MASLD/fatty liver, cirrhosis, liver cancer, or other disease, and it does not provide an oral chlorine-dioxide protocol. Chronic hepatitis B, cirrhosis and liver cancer can have serious or life-threatening consequences and warrant qualified medical evaluation and appropriate treatment.